PT-141: clinical desire findings
Bremelanotide has a clinical trial record. The interesting work starts with the outcomes that record actually contains.
RECONNECT outcomes
The two randomized Phase 3 RECONNECT trials enrolled 1,267 premenopausal women with acquired, generalized HSDD and followed outcomes over 24 weeks. Bremelanotide improved sexual desire and reduced desire-related distress versus placebo; both coprimary endpoints were met in both trials.
The integrated between-group differences were +0.35 for the FSFI-desire domain and −0.33 for FSDS-DAO item 13, the distress measure, with P<.001 for each. Those figures come from different instruments. They cannot be combined into a single percentage improvement in a person's sexual life.
The measured benefit persuades me; the condition it concerns determines its scope. The trial result covers desire and distress in this population. A more expansive promise about pleasure, relationships or sexual performance would need its own evidence.
MC4R neuroimaging
Bremelanotide is a synthetic cyclic peptide that activates central melanocortin receptors, chiefly MC4R and also MC3R. A randomized, double-blind crossover fMRI study in 31 premenopausal women with HSDD examined how MC4R agonism affected sexual brain processing.
The study found enhanced amygdala–insula connectivity and changes in cerebellar and supplementary-motor activity in response to erotic stimuli, alongside increased self-reported desire for up to 24 hours. Functional MRI measures activity-related changes; the connectivity finding describes relationships between brain regions during the task.
I like the correspondence between a reported experience and a brain-processing result, provided each retains its own name. The female Syrian hamster reward experiment asks another question again: bremelanotide did not enhance conditioned place preference in that animal model. Its negative reward finding coexists with the human desire findings.
Adverse-event frequencies
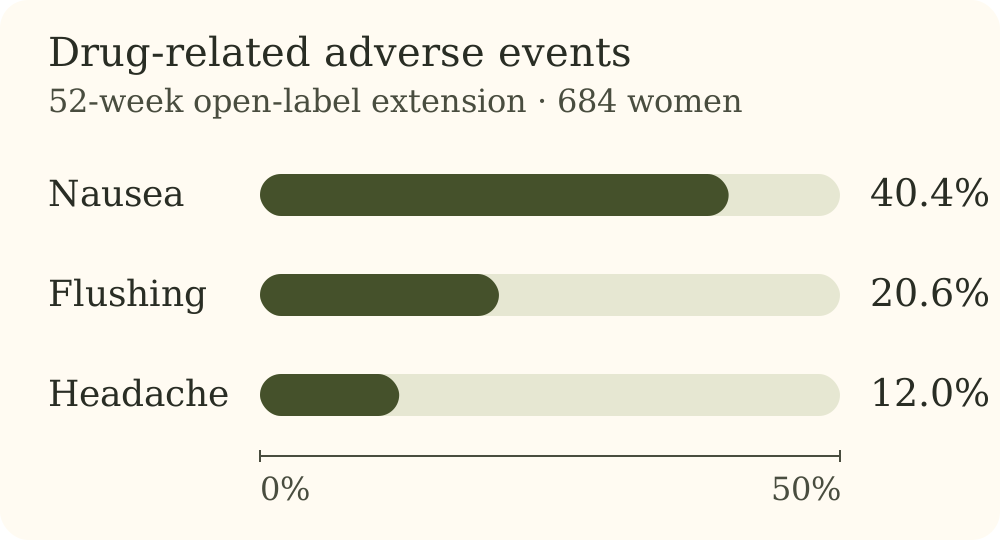
The 52-week open-label extension of RECONNECT enrolled 684 women. Sexual-desire improvements were sustained and no new safety signals emerged. The most common drug-related treatment-emergent adverse events were nausea (40.4%), flushing (20.6%) and headache (12.0%). Nausea was the principal tolerability problem.
Open-label means the treatment was known during that extension. Its sustained findings and longer observation add useful information, while the blinded placebo comparison comes from the earlier trials. I give nausea substantial weight in the account: an improvement in desire and a difficult adverse effect can occur in the same person.
Bremelanotide approval
Bremelanotide injection received FDA approval in 2019 for acquired, generalized HSDD in premenopausal women. The US prescribing information sets that scope. Men, postmenopausal women and sexual-performance enhancement are outside the approved indication. Compounded PT-141 preparations have no FDA approval and require an individual prescribing assessment by a licensed U.S. clinician. Laboratory-only PT-141 material also sits outside the approved pharmaceutical formulation.
The label documents a transient blood-pressure increase and contraindicates use in uncontrolled hypertension or known cardiovascular disease. It also describes focal hyperpigmentation, including changes to skin and gums, which may persist. These warnings merit space alongside the efficacy results, rather than a vague assurance that a peptide is well tolerated.
Reported sexual experiences
People describe greater interest, sensitivity, easier orgasm or a sense of closeness. Other accounts describe nausea, flushing, headache, fatigue, tingling, local irritation or no benefit at all. These reports are anecdotal, not clinical evidence. They cannot establish response rates, interactions or whether a particular preparation caused the experience.
The language is revealing even where it cannot establish efficacy. Wanting, physical arousal, pleasure and connection are distinguishable experiences. Lumping them into a single success story strikes me as unfair to the accounts of non-response. The comparison sets the clinical outcomes alongside kisspeptin's hormone and fertility findings.